

Last updated: October 14, 2026
Most people having minor skin surgery, such as mole, cyst or lipoma removal under local anesthetic, do not need to stop a prescribed blood thinner. Bleeding during these procedures is usually small and controllable with pressure, electrocautery or a stitch, while stopping an anticoagulant or antiplatelet can raise the risk of stroke, heart attack or a blood clot. Every patient's situation is different, and no one should stop or change a prescribed blood thinner without first speaking to the prescribing doctor and the surgeon performing the procedure.
For most mole, cyst, lipoma and skin cancer excisions performed under local anesthetic, blood thinners do not need to be stopped. Dermatologic surgery literature and perioperative guidelines generally treat these procedures as low bleeding-risk, meaning the surgical team can usually control bleeding with pressure, electrocautery or sutures while the patient continues their regular medication [7].
That said, the final decision always rests with the prescribing doctor and the surgeon, based on the specific drug, the procedure site, and the patient's overall health.
No blood thinner should be stopped on a patient's own decision; any stopping or dose change is determined individually by the prescribing doctor in consultation with the surgeon. Commonly discussed medications include ASA (acetylsalicylic acid), clopidogrel, warfarin, apixaban, rivaroxaban, edoxaban and dabigatran, and guidance differs for each one depending on the procedure's bleeding risk [5][7].
There is no universal number of days that applies to every patient or every blood thinner; timing depends on the specific drug's half-life, kidney function, and how much bleeding risk the planned procedure carries. Some perioperative protocols describe omitting a dose of certain anticoagulants the day before a low-risk procedure, while others recommend continuing medication without interruption, but these are examples of reported practice, not fixed rules, and the surgeon and prescribing doctor decide what applies to an individual patient [1][9][13... not cited].
Stopping an anticoagulant or antiplatelet before a minor procedure can increase the risk of stroke, heart attack, or clot formation, which are often more serious outcomes than the bleeding the medication is designed to prevent. This is why many guidelines favour continuing blood thinners through low-bleeding-risk surgery rather than pausing them [3][6].
Reviews of perioperative anticoagulation management report that a broad range of low-bleeding-risk outpatient surgeries and dental procedures can be performed safely while anticoagulation continues, provided the INR (for warfarin) is within the therapeutic range [3]. For warfarin specifically, dermatology-focused perioperative guidance recommends continuing the medication for minor skin surgery, including Mohs micrographic surgery, while targeting an INR at or below 3.0 and relying on local measures to control bleeding, rather than stopping the drug [7].
What happens if you don't stop blood thinners before minor surgery? In most cases, nothing unusual happens. The surgical team manages bleeding directly during the procedure using pressure, electrocautery or sutures, and a hematoma (a collection of blood under the skin) is treated as a recognized, manageable complication rather than an emergency. Patients should still disclose every medication so the team can plan accordingly.
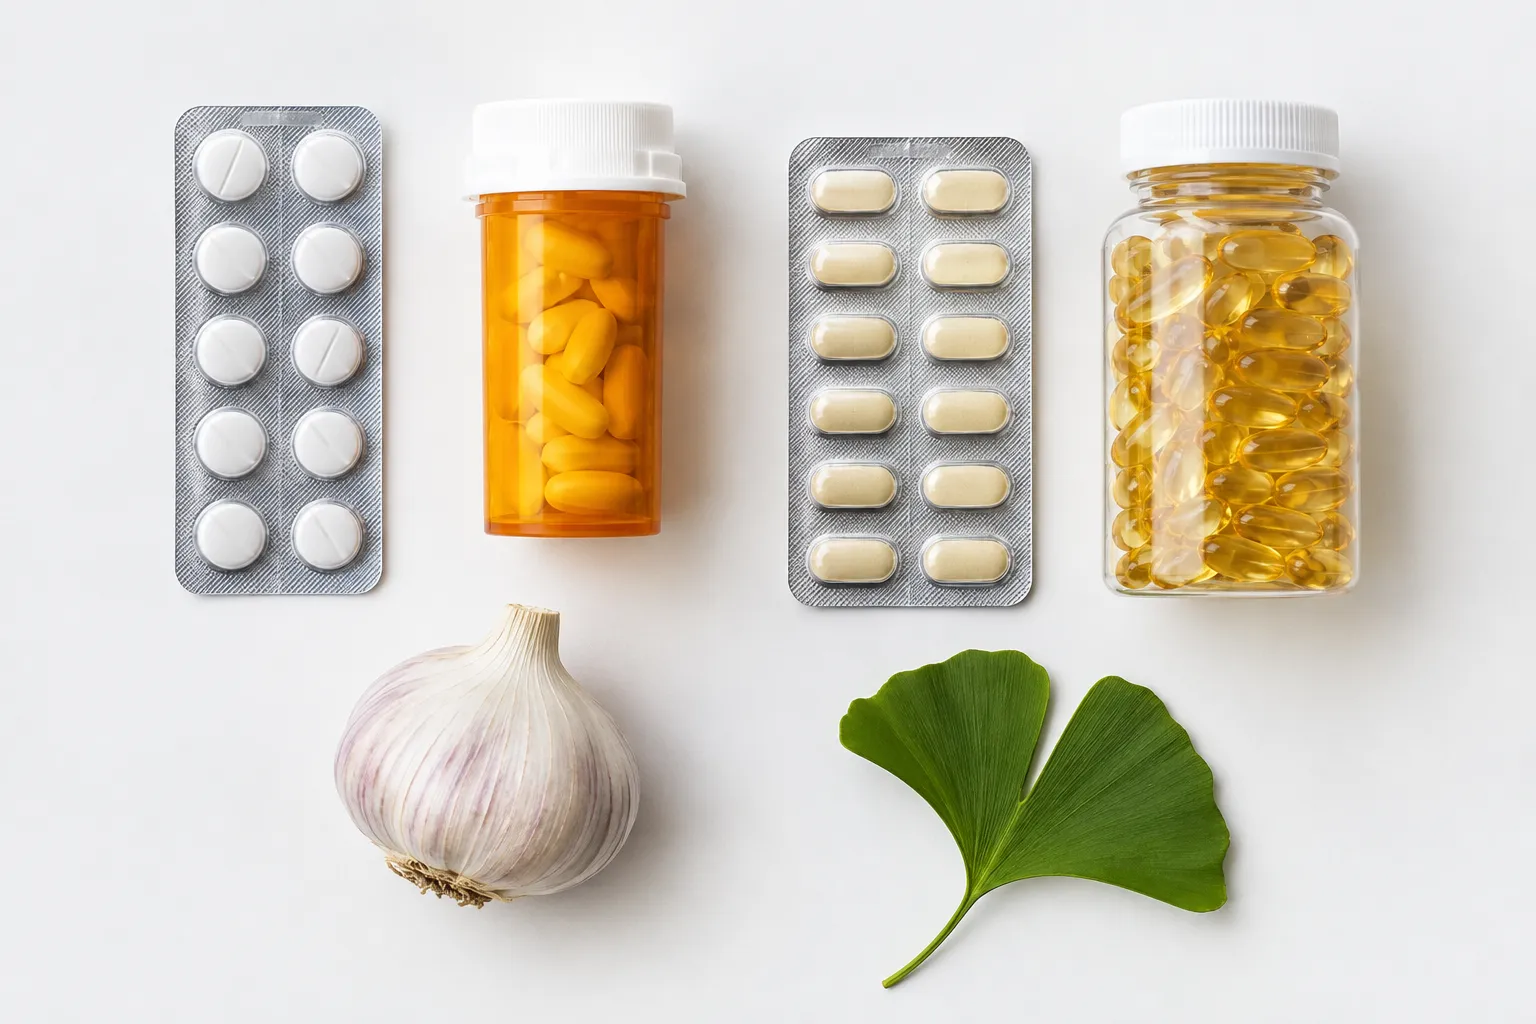
Several categories of medications and supplements can increase bleeding risk during minor surgery, and each should be disclosed to the surgical team regardless of whether it is prescribed or purchased independently. The table below groups common examples by category.
CategoryCommon examplesWhat to tell the surgeonAntiplateletsASA (aspirin), clopidogrelDose, reason prescribed, who prescribed itAnticoagulantsWarfarin, apixaban, rivaroxaban, edoxaban, dabigatranDrug name, dose, last dose timing, recent INR if on warfarinNSAIDsIbuprofen, naproxenHow often taken, whether self-directed or prescribedSupplementsFish oil, vitamin E, ginkgo, garlicAll supplements, even if "natural"
Guidance that applies to one patient's warfarin, apixaban or clopidogrel may not apply to another patient on the same drug, because the decision depends on kidney function, the procedure's bleeding risk, and the patient's clot risk. Dermatology-specific guidance updated in 2026 generally supports continuing warfarin, ASA and clopidogrel for minor skin surgery [7], while direct oral anticoagulant protocols assess the drug's half-life and the patient's renal function before deciding whether to continue or pause dosing around a procedure [5].
Whether to pause apixaban (brand name Eliquis) before a minor procedure is a decision made by the prescribing doctor, not something to decide independently. Some perioperative protocols describe omitting doses of apixaban or rivaroxaban around low- to moderate-bleeding-risk procedures in patients with normal kidney function, without using injectable bridging medication beforehand [5][10], but this reported practice is not a rule for every patient, the surgeon and prescriber decide based on individual risk factors.
Some perioperative protocols suggest omitting an oral anticoagulant dose the morning of a procedure, while others recommend continuing the usual schedule; the correct approach depends on the specific drug and procedure. One multi-society consensus document discusses omitting only the evening dose before minor procedures so the last dose falls roughly a day before the intervention, extending the gap further if bleeding risk or kidney impairment is present [9]. Patients should confirm the exact plan with the prescribing doctor and surgeon well before the appointment, not on the morning of surgery.
Self-directed, over-the-counter aspirin taken for general health reasons (not prescribed for a heart or stroke condition) is often easier to pause before minor surgery than a prescribed antiplatelet, but patients should still confirm this with a doctor or pharmacist rather than assuming it is safe to stop. Can I take aspirin before minor surgery? If aspirin was started independently and is not protecting against a cardiovascular condition diagnosed by a doctor, many patients can pause it temporarily; if it was prescribed after a heart attack, stroke, or stent placement, it should not be stopped without the prescriber's input, since stopping cardioprotective ASA carries its own clot risk [6].
Can you take ibuprofen if you're on blood thinners before surgery? NSAIDs such as ibuprofen and naproxen add to bleeding risk when combined with a prescribed anticoagulant or antiplatelet, so these are generally avoided around the time of a procedure unless a doctor specifically approves their use. Acetaminophen is commonly used instead for pain relief in patients on blood thinners, but patients should confirm pain-control options with the clinical team performing their cyst, mole or lipoma removal.
Many low-bleeding-risk outpatient procedures, including dermatologic excisions, some dental work, cataract surgery and pacemaker implantation, are commonly performed without interrupting warfarin or other anticoagulants, according to perioperative management literature [3][6]. Mole, cyst, lipoma and skin cancer removal under local anesthetic generally fall into this low-risk category, meaning continuation of a prescribed blood thinner is often reasonable, subject to the surgeon's individual assessment.
Dental extractions and similar low-bleeding-risk dental procedures are frequently performed while warfarin continues, provided the INR is within the therapeutic range, according to perioperative anticoagulation reviews [3]. This comparison is useful context for skin surgery patients: if dentistry, which also involves cutting tissue, can often proceed without pausing warfarin, it illustrates why many dermatologic procedures are approached the same way, though the final decision for any patient remains individualized.
Bridge therapy means temporarily replacing an oral anticoagulant with an injectable medication, usually low-molecular-weight heparin, during a planned pause in the oral drug, to reduce the time a patient spends without any anticoagulant protection. Bridging is generally reserved for patients at high risk of clotting who need a longer interruption of warfarin for a higher-bleeding-risk surgery; it is typically avoided for direct oral anticoagulants because their predictable, shorter half-life usually makes bridging unnecessary [2][10]. For minor skin surgery, bridging is rarely required because the standard approach is to continue the blood thinner rather than stop it at all [3][6].
Warfarin management relies on INR blood testing to confirm the degree of anticoagulation, while direct oral anticoagulants (DOACs) such as apixaban, rivaroxaban, edoxaban and dabigatran are managed using dosing schedules and kidney function rather than routine blood tests. This is the core difference patients should understand: what's the difference between stopping warfarin vs dabigatran before surgery?
Neither comparison is a universal instruction. The surgeon and prescribing doctor review the specific drug, procedure and patient history before deciding anything.
Before any mole, cyst, lipoma or skin cancer removal, patients should give the surgical team a complete and accurate list of every medication and supplement they take, including non-prescription products. This allows the team to plan the technique and aftercare appropriately.
A useful pre-visit checklist includes:
The Minor Surgery Center reviews each patient's medication list before mole, cyst, lipoma and skin cancer removal; details on this intake process are explained in the frequently asked questions and in the overview of same-day surgery and what to expect.
On the day of surgery, the surgical team manages any extra bleeding risk from a blood thinner using standard techniques rather than requiring the patient to have stopped the medication. These techniques are the same tools used in most minor skin procedures, adjusted slightly for patients on anticoagulants or antiplatelets.
How do doctors manage bleeding risk during surgery on blood thinners? Common measures include:
Patients often ask whether the local anesthetic injection itself is affected by blood thinners. For a description of what the local anesthetic experience feels like during a cyst removal, see the cyst removal and local anesthetic guide.
Blood thinner reversal is a hospital-based intervention used for emergency or urgent surgery when there is no time to wait for a medication to clear the body, and it does not apply to scheduled, elective minor skin procedures. Reversal agents exist for warfarin and for some DOACs, and they are typically administered in a hospital setting under close monitoring, which is different from the planned, lower-risk environment of a mole, cyst or lipoma removal performed under local anesthetic. Patients having minor skin surgery can expect their regular blood thinner plan to be set in advance with the prescribing doctor and surgeon, not decided urgently at the last minute.
Most bleeding after minor skin surgery is minor, expected, and manageable at home using pressure and basic wound care, regardless of whether a patient is on a blood thinner. Patients on anticoagulants or antiplatelets may notice slightly more oozing or bruising than someone who is not, but this is usually still within the range the surgical team anticipates.
For step-by-step home care guidance by procedure type, see the mole removal aftercare guide, the cyst wound care instructions, and the overview of possible complications after lipoma removal.
Bleeding that does not slow down after 15 to 20 minutes of firm, direct pressure, or bleeding that soaks through multiple dressings, is a reason to contact the clinic or seek medical attention promptly. A hematoma, which is a firm, painful swelling under the skin from pooled blood, should also be reported to the surgical team rather than managed alone.
Other warning signs include increasing pain instead of gradual improvement, spreading redness, fever, or a wound that reopens. Patients on anticoagulants or antiplatelets should have a clear plan, given at discharge, for who to call if bleeding does not settle with standard home measures.
Can I stop my blood thinner myself before mole or cyst removal?
No. Patients should never stop, skip, or adjust a prescribed anticoagulant or antiplatelet without first discussing it with the prescribing doctor and the surgeon performing the procedure, since stopping carries its own risks.
Is aspirin different from prescription blood thinners for surgery planning?
Self-directed aspirin not prescribed for a diagnosed cardiovascular condition is often easier to pause than a prescribed antiplatelet or anticoagulant, but confirmation from a doctor or pharmacist is still recommended before any change.
Do supplements like fish oil or garlic need to be disclosed before surgery?
Yes. Fish oil, vitamin E, ginkgo and garlic can all affect bleeding and should be listed along with prescription medications when discussing a mole, cyst, lipoma or skin cancer removal.
Will being on a blood thinner change how my surgery is performed?
Possibly in minor ways, such as additional use of electrocautery, extra sutures, or a slightly longer observation period after the procedure, but the overall approach to mole, cyst or lipoma removal generally stays the same.
How soon can I restart my blood thinner after minor skin surgery?
Timing varies by drug and by procedure; some protocols describe restarting certain medications within hours of a low-risk procedure once bleeding is controlled, while others wait longer, but this decision is made by the prescribing doctor based on the individual case [4][8].
What if I am not sure whether my medication counts as a blood thinner?
Bring the full medication list, including bottles if possible, to the pre-surgery discussion so the clinical team can identify any anticoagulant, antiplatelet, or NSAID that may affect bleeding risk.
Most patients booked for mole, cyst, lipoma or skin cancer removal under local anesthetic can continue their prescribed blood thinner, because the bleeding risk of these procedures is usually small and manageable with standard surgical techniques, while interrupting anticoagulation carries its own risks. Decisions about ASA, warfarin, apixaban, rivaroxaban, edoxaban, dabigatran or clopidogrel are individualized and must be made jointly by the prescribing doctor and the surgeon, never by the patient alone.
Next steps: list every medication and supplement before the pre-surgery discussion, confirm the plan directly with the prescribing doctor, and bring any recent INR results if taking warfarin. This article provides general information only and is not medical advice; any change to a blood thinner must be made in consultation with the prescribing physician.
[1] Nch Provider Educ Noacs Perioperative Mgmt - https://www.heart.org/-/media/Files/Professional/Quality-Improvement/Get-With-the-Guidelines/Get-With-The-Guidelines-AFIB/Anticoagulation-Toolkit/NCH-Provider-Educ-NOACs-PeriOperative-Mgmt.docx
[2] Bridging Anticoagulation August 2025 - https://www.dbth.nhs.uk/wp-content/uploads/2025/08/Bridging-Anticoagulation-August-2025.pdf
[3] 4 How I Tx Anticoagd Patients - https://www.acc.org/~/media/Non-Clinical/Files-PDFs-Excel-MS-Word-etc/Tools%20and%20Practice%20Support/Quality%20Programs/Anticoagulation-roundtable/4-How-I-Tx-anticoagd-patients.pdf
[4] Nbk557590 - https://www.ncbi.nlm.nih.gov/books/NBK557590/
[5] Pmc12240022 - https://pmc.ncbi.nlm.nih.gov/articles/PMC12240022/
[6] Chest Releases Clinical Practice Guideline On Perioperative Management Of Antithrombotic Therapy - https://www.chestnet.org/newsroom/press-releases/2022/08/chest-releases-clinical-practice-guideline-on-perioperative-management-of-antithrombotic-therapy
[7] Dermatology - https://health.ucsd.edu/for-health-care-professionals/anticoagulation-guidelines/perioperative/procedure-recommendations/dermatology/
[8] Management Plan For Patients On Warfarin And Doacs In The Peri Operative Period - https://handbook.ggcmedicines.org.uk/guidelines/cardiovascular-system/management-plan-for-patients-on-warfarin-and-doacs-in-the-peri-operative-period/
[9] Perioperatief Beleid Bloedverdunners 2025 - https://www.stlucas.be/media/2s4fycci/perioperatief-beleid-bloedverdunners-2025.pdf
[10] Bsh Periop Guideline For Editor - https://b-s-h.org.uk/media/2639/bsh_periop_guideline_for_editor.pdf
Medical disclaimer: This article is general information only and is not medical advice. It does not replace an individual assessment by a physician. Any decision to continue, pause, or change a prescribed anticoagulant or antiplatelet medication before minor surgery must be made with the prescribing doctor and the surgeon performing the procedure.





