

Last updated: October 6, 2026
BCC on the eyelid is a basal cell carcinoma, the most common type of malignant eyelid tumor, that grows slowly along the eyelid margin or inner corner of the eye and rarely spreads to distant organs but can destroy surrounding eyelid tissue if left untreated [8]. Treatment is almost always surgical, with Mohs micrographic surgery or margin-controlled excision as the gold standard, achieving reported cure rates between 80% and 99% [7][10]. Catching it early keeps treatment simpler, preserves more eyelid tissue, and lowers the chance of recurrence.
BCC on the eyelid is a basal cell carcinoma that originates in the basal layer of the skin covering the eyelid, most often near the eyelid margin or the inner corner of the eye. It is a malignant but slow-growing tumor that almost never spreads through the bloodstream, though it can quietly invade nearby structures over months or years.
Basal cell carcinoma accounts for the large majority of eyelid cancers in most studied populations, with one recent series reporting it in nearly 58% of all eyelid malignancies, far ahead of sebaceous gland carcinoma and other rarer tumors [8]. It develops from basal keratinocytes, the cells that sit at the base of the epidermis and normally replace skin cells as they shed. When ultraviolet damage or other triggers cause these cells to divide abnormally, a tumor forms.
Unlike melanoma, BCC does not arise from pigment-producing cells, and unlike squamous cell carcinoma, it does not typically scale or crust early on. For a broader orientation on how BCC fits among other skin malignancies, see this overview of skin cancers explained.
BCC on the eyelid is almost always a local problem, not a systemic one, the danger lies in what it destroys nearby, not where it travels.
Choose to treat BCC on the eyelid as urgent (not emergency) if: the lesion has been present for more than a few weeks, keeps bleeding or crusting, or sits within a few millimeters of the eyelid margin or tear duct, these locations have less room for the tumor to grow before affecting eye function.
Basal cell carcinoma on the eyelid develops mainly from cumulative ultraviolet (UV) exposure over a lifetime, combined with individual risk factors such as fair skin, older age, and a history of sunburns. No single sun exposure event causes it; it is the result of years of DNA damage to skin cells that eventually triggers uncontrolled growth.
Recognized risk factors include:
The eyelid skin is thin and gets significant cumulative sun exposure, yet people often protect it less than other facial areas (sunglasses and hats help, but eyelid-specific sunscreen application is frequently skipped). This combination of thin, UV-exposed skin and under-protection partly explains why the eyelid is a common BCC site despite its small surface area.
Common mistake: assuming that because eyelid skin is thin and delicate, a new bump there is more likely to be benign (a stye, cyst, or milium) than cancer. Thin skin does not protect against BCC, it is actually one of the more frequently affected facial sites.
Early BCC on the eyelid typically presents as a small, slow-growing, painless nodule near the eyelid margin or inner corner of the eye that does not heal on its own after several weeks. This slow, non-resolving nature is the single most telling early clue, distinguishing it from styes, cysts, or irritation that typically resolve within days.
Common features clinicians look for include:

These features are consistent across recent clinical guidance and reviews describing typical eyelid BCC presentation [4][7][8]. For a visual sense of how these signs compare with other skin findings, see this guide to skin cancer symptoms and pictures and the broader list of seven warning signs of skin cancer.
Edge case: infiltrative and morpheaform BCC subtypes often lack the classic pearly nodule appearance. They can look like a subtle, pale, scar-like thickening of the skin with no clear border, a presentation that is easy to dismiss and is one reason these subtypes carry a higher risk of being diagnosed late [3][7].
A simple decision rule: any eyelid lesion that persists beyond 4 to 6 weeks, recurs after apparent healing, or involves eyelash loss deserves a specialist look, regardless of how small or painless it seems. Periodic self-checks help catch these changes early, see this practical skin cancer self-exam and check guide for a simple routine.
The standard treatment for BCC on the eyelid is complete surgical removal with histologic confirmation that all cancer cells have been cleared from the margins, most commonly done through Mohs micrographic surgery or frozen-section-controlled excision. This margin-controlled approach is described as the gold standard across recent clinical literature on periocular BCC [2][10].
Main treatment options, in order of how commonly they are used:
Choosing between Mohs surgery and standard excision for BCC on the eyelid comes down to tumor location, histologic subtype, and whether the tumor is primary or recurrent. Mohs is generally preferred when the tumor sits near the medial canthus, has an aggressive growth pattern, or has recurred after prior treatment, because it offers the most tissue-sparing way to confirm clear margins [7].
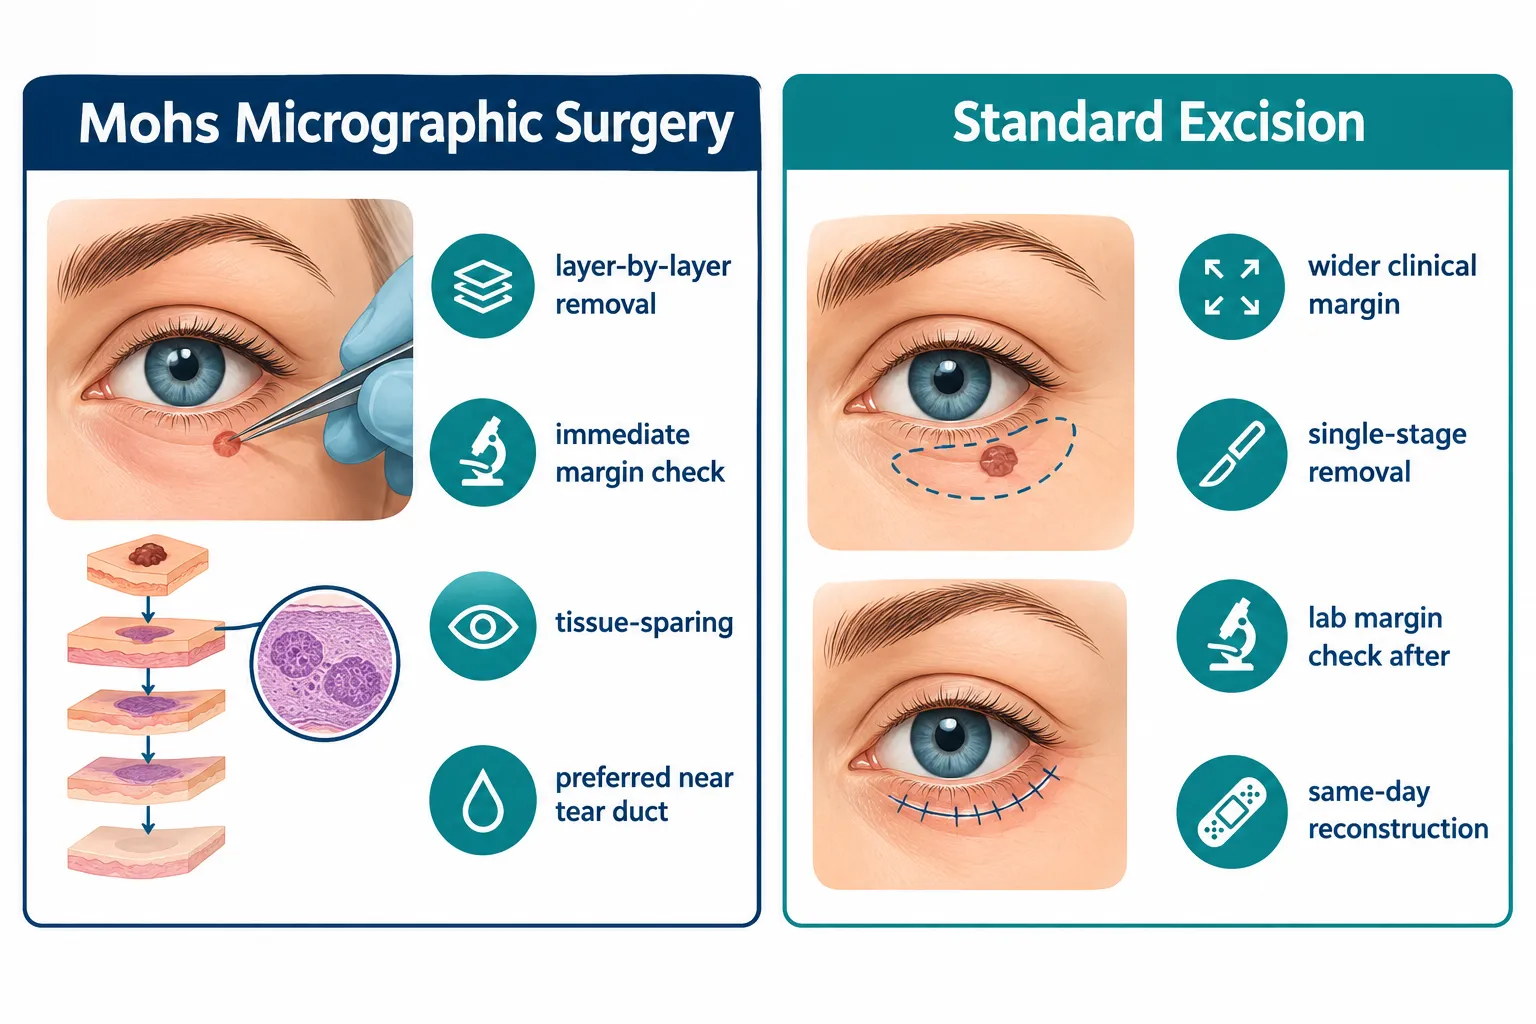
FactorMohs Micrographic SurgeryStandard ExcisionMargin checkingReal-time, layer by layer, during surgerySent to lab after surgery, results days laterTissue sparingHigh, removes minimum tissue neededModerate, wider margin taken upfrontBest suited forMedial canthus, recurrent tumors, aggressive subtypesWell-defined, low-risk, primary tumorsReconstruction timingOften same day once margins confirmed clearMay be same day or delayed pending lab results
Decision rule: choose Mohs if the tumor is at the medial canthus, has recurred, or has an infiltrative/morpheaform pattern on biopsy. Choose standard margin-controlled excision if the tumor is small, nodular, well-defined, and located away from the tear duct and lid margin [2][7].
The cost of BCC on the eyelid surgery depends on the technique used, whether reconstruction is needed, and the healthcare setting, with Mohs surgery and eyelid reconstruction typically costing more than a simple standard excision due to the extra surgical time and specialized skill involved. In Canada, medically necessary skin cancer removal is often covered under provincial health plans when a biopsy confirms malignancy, though cosmetic refinements or specific reconstruction techniques may carry additional fees depending on the clinic and province.
Factors that influence overall cost include:
Because pricing varies by provider, region, and individual case complexity, the most reliable way to get an accurate estimate is a direct consultation after biopsy confirmation. Clinics experienced in periocular skin cancer removal, such as those profiled in this guide to the best skin cancer clinics in Toronto, can outline expected costs once imaging and biopsy results are available.
Quick example: a small, well-defined lower eyelid BCC treated with single-stage excision and primary closure is generally less costly and faster than a medial canthus tumor requiring multi-stage Mohs surgery followed by flap reconstruction, the complexity of rebuilding eyelid structure, not just removing the tumor, is what drives cost up.
A BCC on the eyelid removal procedure typically takes between 1 and 3 hours total, including tumor removal, margin checking, and immediate reconstruction, though Mohs surgery can take longer if multiple tissue layers need to be checked before margins are clear. Recovery from swelling and bruising generally takes 1 to 3 weeks, while final scar maturation can take several months.
A typical timeline looks like this:
Common mistake: expecting to return to normal activities the next day. Even with same-day discharge, patients should plan for several days of limited activity, cold compress use, and avoiding eye makeup or contact lenses until the surgical site is fully healed.
BCC on the eyelid very rarely spreads to distant organs (metastasis), but it can spread locally into deeper eyelid tissue, the tear drainage system, and, if neglected long enough, into the orbit (eye socket) or sinuses. This local, invasive growth pattern, rather than distant spread, is the main danger of untreated eyelid BCC.
Key points on spread risk:
Edge case: a BCC that looks small on the surface can still have roots extending well beyond what is visible, particularly in infiltrative or morpheaform subtypes. This is one reason margin-controlled surgery, rather than a simple visual excision, is preferred for eyelid tumors, the microscope can detect spread the eye cannot.
BCC on the eyelid and squamous cell carcinoma (SCC) of the eyelid are both common periocular skin cancers, but they differ in appearance, growth speed, and risk of spread, BCC grows slowly and rarely metastasizes, while SCC grows faster and carries a higher (though still relatively low) risk of spreading to lymph nodes.

FeatureBCCSquamous Cell CarcinomaTypical appearancePearly nodule, rolled border, surface blood vesselsScaly, crusted, often ulcerated plaqueGrowth rateSlow, over months to yearsFaster, over weeks to monthsSpread riskVery low metastasis riskHigher risk of lymph node spread than BCCTreatment approachSurgical excision/Mohs, same principleSurgical excision/Mohs, same principle
Both cancers are diagnosed by biopsy, not appearance alone, since the two can look similar in early stages. For a closer look at squamous cell carcinoma specifically, see this overview of squamous cell carcinoma. Melanoma, by contrast, usually presents as a pigmented, irregular lesion rather than the pearly or scaly patterns seen in BCC and SCC, more detail is available in this melanoma overview.
Decision rule: any eyelid lesion that is scaly, crusted, and growing noticeably faster than a typical slow nodule should be evaluated with SCC specifically in mind, since it changes the urgency and sometimes the surgical margin needed.
Home remedies do not cure BCC on the eyelid. No topical cream, natural oil, or over-the-counter product has been shown to eliminate basal cell carcinoma on the eyelid, and delaying proper treatment in favor of home remedies allows the tumor more time to invade deeper eyelid and orbital tissue.
A few important clarifications:
Common mistake: confusing a slow-growing, painless BCC with a benign skin issue that might resolve with moisturizing or gentle care. Because eyelid BCC rarely causes pain, people sometimes delay seeking care for months, assuming it will go away, it will not.
The prognosis for BCC on the eyelid is generally excellent when treated early with complete surgical removal, with reported cure rates for surgical management, including Mohs surgery, ranging from about 80% to 99% in clinical series [7]. Because BCC rarely metastasizes, overall survival is high; the main prognostic concern is local tissue damage and functional impact on the eyelid, not life-threatening spread.
Factors that influence prognosis:
A 2025 systematic review and meta-analysis on ocular and periocular BCC confirms that nodular BCC remains the most frequently diagnosed subtype in this region, which is reassuring since nodular tumors are generally easier to treat completely and carry a more favorable outlook than aggressive subtypes [6].
Untreated BCC on the eyelid continues to grow locally, gradually destroying eyelid tissue, eyelashes, and eventually deeper structures such as the tear drainage system, eye socket, and in severe long-standing cases, surrounding bone or sinus tissue. The longer treatment is delayed, the larger and more complex the eventual surgery and reconstruction tend to be.
Consequences of leaving eyelid BCC untreated can include:
Edge case: a chronically ulcerated, non-healing eyelid lesion that has been present for an extended period without treatment should be evaluated not only for tumor extent but also for secondary infection or infestation, since open wounds in this area can attract complications unrelated to the cancer's direct growth [5].
Recurrence rates for BCC on the eyelid vary mainly by treatment method and tumor risk features, with margin-controlled techniques like Mohs surgery generally associated with lower recurrence than simple excision without intraoperative margin checking, especially for high-risk or recurrent tumors [7]. Aggressive histologic subtypes, narrow surgical margins, and tumors at the medial canthus all raise the chance of recurrence.
Factors that raise recurrence risk:
Because the eyelid is considered a high-risk recurrence site, follow-up schedules tend to be more frequent than for BCC on other body areas. One recent clinical guideline recommends follow-up every 3 to 4 months during the first year after treatment, every 6 months for the next 2 to 3 years, and annually thereafter for lower-risk patients [7]. For patients with high-risk features, narrow margins, recurrent disease, or aggressive subtypes, a minimum of 5 years of clinical surveillance is advised [2].
Decision rule: choose more frequent follow-up (every 3-4 months) if the tumor had aggressive histology, involved the medial canthus, or required more than one surgical stage to clear margins. Standard annual follow-up may be reasonable for small, nodular, clearly-margined tumors treated successfully in a single stage.
Preventing BCC on the eyelid centers on consistent, lifelong sun protection for the periocular area, since cumulative UV exposure is the primary driver of this cancer. Because eyelid skin is thin and frequently under-protected compared with the rest of the face, deliberate protection habits matter more here than many people realize.
Practical prevention steps include:
Routine screening is especially useful for people with risk factors. Programs such as skin cancer screening in Ontario offer a structured way to catch suspicious lesions, including eyelid lesions, before they progress. Reviewing the general seven warning signs of skin cancer alongside eyelid-specific signs can help build a consistent self-check habit.
Quick example: someone who wears UV-blocking sunglasses daily but skips sunscreen on the eyelids themselves is still leaving a thin, high-exposure area unprotected, both habits are needed together, not one or the other.
Diagnosis of BCC on the eyelid requires a tissue biopsy, since visual inspection alone, even by an experienced clinician, cannot reliably distinguish BCC from other eyelid conditions or from squamous cell carcinoma. A punch biopsy is usually adequate for small, well-demarcated lesions, while imaging such as CT or MRI is added when deeper orbital or bone involvement is suspected [2][7].
Diagnostic steps typically include:
Studies also note only moderate agreement between initial clinical impression and final histopathological diagnosis for eyelid tumors, reinforcing why biopsy-based confirmation, not appearance alone, should guide every treatment decision [8].
Is BCC on the eyelid dangerous?
BCC on the eyelid is rarely life-threatening because it almost never spreads to distant organs, but it can be locally dangerous, destroying eyelid tissue and, if neglected, invading the eye socket or tear duct system over time.
What does early BCC on the eyelid look like?
Early BCC on the eyelid usually looks like a small, painless, pearly or waxy bump near the eyelid margin, sometimes with tiny visible blood vessels or mild eyelash loss, that does not heal within several weeks.
Can BCC on the eyelid be removed without surgery?
Surgery is the standard treatment for eyelid BCC; non-surgical options like topical medication or radiation are generally reserved for patients who cannot undergo surgery, since they offer less reliable margin control in this delicate area [1][4].
How painful is BCC eyelid removal surgery?
The procedure itself is performed under local anesthesia, so pain during surgery is minimal; mild discomfort, swelling, and bruising afterward are common and typically manageable with over-the-counter pain relief and cold compresses.
Does insurance or public health coverage pay for BCC eyelid removal?
In Canada, medically necessary removal of a biopsy-confirmed skin cancer is typically covered under provincial health insurance, though coverage details and any additional reconstruction costs can vary by province and clinic.
How long is recovery after BCC eyelid surgery?
Initial swelling and bruising usually improve within 1 to 3 weeks, while complete scar maturation and final eyelid appearance can take several months to fully settle.
Can BCC on the eyelid come back after treatment?
Yes, recurrence is possible, especially with aggressive histologic subtypes, narrow surgical margins, or medial canthus location, which is why structured long-term follow-up is recommended after treatment [7][2].
Is BCC on the eyelid the same as a stye or chalazion?
No. Styes and chalazia are inflammatory or blocked-gland conditions that typically resolve within days to a few weeks, while BCC is a slow-growing malignant tumor that does not resolve on its own and often shows pearly, telangiectatic features rather than simple redness and swelling.
Who is most at risk for BCC on the eyelid?
People over 50 with fair skin, a history of frequent sunburns, significant lifetime sun exposure, immunosuppression, or certain genetic syndromes face the highest risk of developing BCC on the eyelid.
Does BCC on the eyelid always need reconstruction after removal?
Most cases require some form of eyelid reconstruction after tumor removal to restore normal eyelid closure and tear drainage function, ranging from simple direct closure for small defects to flaps or grafts for larger ones.
BCC on the eyelid is a common but manageable form of skin cancer when it is caught and treated early. It rarely threatens life because it almost never spreads beyond the local area, but it can quietly damage eyelid tissue, eyelashes, and even the eye socket if ignored for too long. The path forward is straightforward: get any persistent, non-healing eyelid bump checked, insist on a biopsy rather than a visual guess, and choose margin-controlled surgery, Mohs or frozen-section excision, as the definitive treatment.
Next steps worth taking now:
Acting early on a suspicious eyelid lesion almost always means a simpler surgery, less reconstruction, and a better long-term outcome.
[1] Full - https://www.frontiersin.org/journals/oncology-reviews/articles/10.4081/oncol.2020.420/full
[2] Html - https://fomm.amegroups.org/article/view/61980/html
[3] S00417 025 06807 8 - https://link.springer.com/content/pdf/10.1007/s00417-025-06807-8?pdf=openurl&error=cookies_not_supported&code=6ee5c780-fed6-456f-8fb0-4d2fe99647c6
[4] Basalcellcarcinoma Bcc Periocular - https://www.college-optometrists.org/clinical-guidance/clinical-management-guidelines/basalcellcarcinoma_bcc_periocular
[5] Ophthalmomyiasis And Basal Cell Carcinoma A Review - https://esmed.org/ophthalmomyiasis-and-basal-cell-carcinoma-a-review/
[6] pubmed.ncbi.nlm.nih.gov - https://pubmed.ncbi.nlm.nih.gov/40428237/
[7] ijooo - https://ijooo.org/archive/volume/11/issue/2/article/24373/pdf
[8] ijooo - https://ijooo.org/archive/volume/11/issue/2/article/24381/pdf
[9] N4lxtzqqjxg3wtny3xr3bss - https://www.scielo.br/j/abd/a/N4LXTzqqjxg3wTNy3xR3BSs/?format=pdf&lang=en
[10] Html - https://aes.amegroups.org/article/view/5914/html





